Updated October 6, 2026 with ApoB treatment goals and testing guidance.
In Empirical Health’s analysis of 1,710 patients with both LDL cholesterol and ApoB measured, 8% had elevated ApoB (≥100 mg/dL) despite LDL below 130 mg/dL. Looking at LDL alone wouldn’t flag their elevated ApoB. These were our analysis cutoffs, not treatment goals for everyone.
An ApoB blood test measures a protein carried by cholesterol particles that can build up in artery walls. It helps reveal when your blood contains more of those particles than your LDL cholesterol suggests. The 2026 ACC/AHA dyslipidemia guidelines include ApoB treatment goals and support selective testing to guide care, especially when diabetes or high triglycerides complicate the picture.
Here’s how to interpret your ApoB result, choose a treatment goal with your clinician, and get tested.
What is a normal ApoB level?
An ApoB below 90 mg/dL is considered desirable in Mayo Clinic Laboratories’ adult reference categories:
| ApoB (mg/dL) | Adult result category |
|---|---|
| Below 90 | Desirable |
| 90–99 | Above desirable |
| 100–119 | Borderline high |
| 120–139 | High |
| 140 or higher | Very high |
Labs may use different reference ranges. Your treatment goal can be lower than the cutoff printed on your report, depending on your cardiovascular risk.
What are the 2026 ACC/AHA ApoB treatment goals?
The 2026 ACC/AHA guidelines include ApoB goals below 90, 70, or 55 mg/dL. Examples include:
| Clinical situation | ApoB goal |
|---|---|
| Diabetes without additional cardiovascular risk factors or diabetes-specific risk modifiers | Below 90 mg/dL |
| Diabetes with additional risk factors, or established atherosclerotic cardiovascular disease that isn’t very high risk | Below 70 mg/dL |
| Established atherosclerotic cardiovascular disease at very high risk | Below 55 mg/dL |
These are selected examples, not every guideline category. Your clinician considers your history, other lipid results, and treatment when choosing a goal. An ApoB of 85 mg/dL can be desirable on a lab report yet above a goal of 70 mg/dL.
What does a high ApoB result mean?
High ApoB suggests more plaque-forming particles in your blood. It raises concern about cardiovascular risk even when LDL looks normal, but doesn’t by itself diagnose blocked arteries. Contributors can include inherited lipid disorders, insulin resistance, diet, and hypothyroidism. Review the result alongside your lipid panel and medical history, then agree on a goal and a plan to lower ApoB.
What are lipoproteins? Why is ApoB atherogenic?
Lipoproteins are molecules in your blood made of fats (e.g. cholesterol, triglycerides) and proteins. They’re critical for many physiological processes, like hormone production, bile acid synthesis, and cell membrane formation.
However, at excess quantities, some lipoproteins are atherogenic—meaning they can enter your arterial walls, form plaques, and cause heart attacks.
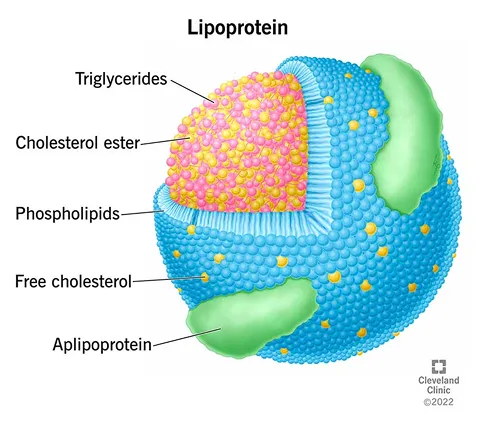
A lipoprotein. Source: Cleveland Clinic
Which lipoproteins contain ApoB (and increase cardiovascular risk)
ApoB stands for Apolipoprotein B.
An apolipoprotein is the green blob in the image above. It’s a protein wrapper around a lipoprotein that helps make it soluble in plasma, maintains its structure, and helps with binding during tissue uptake.
There are four main atherogenic lipoproteins:
| Lipoprotein | Function | Size |
|---|---|---|
| vLDL: Very Low-Density Lipoprotein | Triglyceride transport | Large |
| IDL: Intermediate-Density Lipoprotein | Intermediate LDL precursor | Medium |
| LDL: Low-Density Lipoprotein | Deliver cholesterol to cells | Small |
| Lipoprotein(a) | Deliver cholesterol to cells | Small |
What is the ApoB blood test?
An ApoB blood test measures the concentration of apolipoprotein B (ApoB) in your blood. Since each atherogenic lipoprotein particle carries exactly one ApoB molecule, the test is a good indicator of the total number of atherogenic particles—and thus your cardiovascular risk.
Lipid panels vs ApoB
A standard lipid panel in the U.S. includes:
- Total cholesterol
- HDL
- Triglycerides
- LDL-C
- Cholesterol/HDLC Ratio
- LDL/HDL Ratio
- Non HDL Cholesterol
You’ll notice it doesn’t include ApoB. One reason for this is increased cost vs. other countries, but the end result is that treatment for high cholesterol is mostly based on LDL-C in the U.S.
As mentioned in a previous post about predicting your risk of a heart attack, the LDL-C value on your lipid panel is not measured directly, it’s estimated using the Friedewald equation:
LDL-C = Total Cholesterol - HDL Cholesterol - (Triglyceride / 5)Your LDL-C (LDL-calculated) estimates the mass of cholesterol carried by LDL particles in one deciliter of blood. There are several limitations to this estimate:
- Inaccurate at high and low triglyceride levels (> 400 mg/dL or <100 mg/dL)
- Assumes that the ratio of Triglycerides to vLDL cholesterol is 5:1, which isn’t always true
- Ignores cholesterol carried by other atherogenic particles: vLDL, IDL, and Lipoprotein(a)
ApoB vs LDL cholesterol
ApoB is more accurate measure of cardiovascular risk than LDL cholesterol. Evidence shows that the number of atherogenic particles is a better predictor of cardiovascular risk than the cholesterol mass LDL particles. Since even cholesterol-poor LDL particles can be harmful when there are many of them, LDL-C can be an incomplete measure.
Since each atherogenic lipoprotein has exactly one ApoB molecule, measuring ApoB estimates the number of atherogenic particles, and is therefore considered a more accurate measure of cardiovascular risk. More particles = more chances to enter artery walls = higher risk of a blockage.
ApoB vs non-HDL cholesterol
Non-HDL cholesterol is calculated as Total Cholesterol - HDL. ApoB also measures heart disease more accurately than non-HDL cholsterol. A 2012 meta-analysis of 233,455 patients found ApoB predicted cardiovascular events about 13% better than non-HDL cholesterol. Why? Non-HDL cholesterol still measures cholesterol mass rather than particle number, which is the key driver of atherogenesis.
When ApoB and LDL disagree (discordance)
ApoB, LDL, and non-HDL cholesterol are often aligned, but discordance has been found in many scenarios. For example:
- Men, Hispanics, older patients, statin users, and patients with high triglycerides or high BMI showed more discordance (2024 study)
- 20% of women had discordance in this 2017 study
The 2016 CARDIA study quantified the value of ApoB over LDL-C when they diverge. It assessed long-term cardiovascular risk by measuring LDL and ApoB levels in adults aged 18–30, then measured coronary artery calcification (CAC)—a marker of plaque buildup—via CT scan 25 years later. The study found young adults with high ApoB and normal LDL-C had 55% higher odds of developing CAC in the future. Those with high LDL-C and normal ApoB did not show a statistically significant increase in CAC risk.
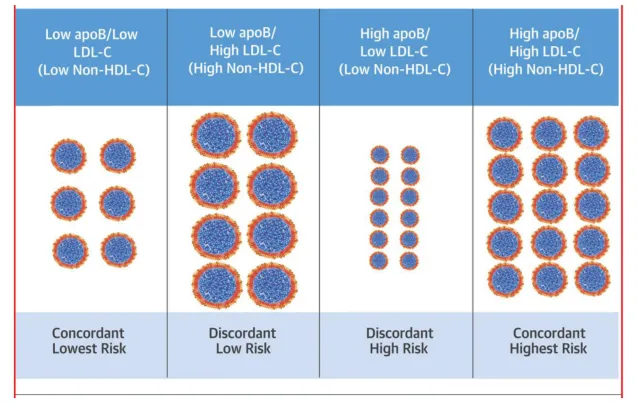
Source: “Discordance Between Apolipoprotein B and LDL-Cholesterol in Young Adults Predicts Coronary Artery Calcification: The CARDIA Study”, Wilkins et al.
Can you have high LDL and low ApoB?
Yes. In a (2021 study), 51% of patients with metabolic syndrome had high LDL-C but normal ApoB. High LDL with low ApoB can happen partly because triglycerides affect the measurement of LDL-C, but not ApoB.
Does insurance cover ApoB testing?
Most health insurance doesn’t cover universal ApoB testing. Medicare’s ApoB testing policy “denies coverage for all CV risk assessment panels, except the basic lipid panel.” Some private insurers, like United Healthcare, cover ApoB in certain circumstances like high tryglerides, diabetes, obesity or metabolic syndrome, for people on lipid therapy, and so on Hypertriglyceridemia (detailed policy.
What ApoB level does Peter Attia recommend?
Note: Empirical Health is not affiliated with Peter Attia
Peter Attia advocates for an ApoB of <60 mg/dL (5th percentile of the population). If possible, he advocates getting it even lower, to about 20-30 mg/dL, although that may not be practical for everyone. Typically, lowering your ApoB to <60 mg/dL would require not only diet and exercise, but also stacking multiple medications (e.g., statins plus PCSK9 inhibitors). Reaching the 5th percentile may not be practical for everyone due to sheer cost (about $5,850 per year for PCSK9 inhibitors). Reaching the 20th percentile of ApoB, about 78 mg/dL, is achievable for most with inexpensive medications. Reaching below the median ApoB, 97 mg/dL, is a population comparison, not a personal treatment target. Peter Attia generally doesn’t recommend an ideal LDL cholesterol: instead he recommends measuring ApoB.
How to lower your ApoB naturally
The good news is that you can reduce your ApoB through nutrition:
- Increase soluble fiber
- Reduce saturated fat
- See also: how to lower your cholesterol in 7 days and normal cholesterol levels for ApoB and LDL targets
(Surprisingly, dietary cholesterol does not have a strong effect on the number of atherogenic particles for most people.)
The mechanism for how your diet affects your ApoB is related to cholesterol metabolism. Your liver extracts ApoB-containing lipoproteins from your blood and uses them to create bile acid. During digestion, these bile acids are secreted into your gut to help break down fats. 95% of bile acids are then reabsorbed so they can be reused.
Eating soluble fiber disrupts this cycle. In the gut, soluble fiber absorbs water and thickens into a gel. This gel physically traps bile acid, prevents it from being reabsorbed back to your liver, and it gets excreted. Your liver then senses less bile acid, so it breaks down more ApoB-containing lipoproteins from your blood to replenish.
Eating saturated fat has the opposite effect. Saturated fats are broken down and absorbed in the gut before reaching the liver. This causes the liver to increase production of vLDL (and eventually LDL) and also reduce the clearing of atherogenic lipoproteins from the blood.
How to lower your ApoB with medication
The primary medications to reduce ApoB are statins. Statins decrease your liver’s synthesis of cholesterol and increase your liver’s removal of LDL particles from the blood. The most common is Atorvastatin (Lipitor), with over 100 million prescriptions filled in the U.S. each year. Statins are remarkably effective, with severe patients seeing a 20-40% reduction in ApoB in just a few months, inexpensive (~$5/mo), and safe, with the most common side effect (muscle pain) occurring in <1% of patients.
Do you need to fast for an ApoB test?
ApoB itself doesn’t require fasting. Other tests ordered with it may have different requirements, so follow the preparation instructions for your complete lab order.
How often should you retest ApoB?
If ApoB is guiding your treatment, your clinician can recheck it with your follow-up lipid panel. The 2026 guidelines recommend a lipid panel 4–12 weeks after starting or adjusting lipid-lowering therapy, then every 6–12 months. ApoB testing at each visit depends on whether it will change your care.
How can you measure your ApoB levels?
Empirical Health’s advanced cardiovascular panel includes ApoB testing, along with a complete lipid panel, and Lipoprotein(a), which is an atherogenic lipoprotein primarily determined by genetics.

What’s the cost of an ApoB lab test?
You can buy ApoB alone or as part of a panel. Labcorp OnDemand lists standalone ApoB at $69, with a $51.75 sale price when checked on October 6, 2026. Empirical Health’s comprehensive health panel costs $190 and includes 100+ biomarkers, including ApoB, a lipid panel, and Lp(a).
A standalone test can be enough if you’re following ApoB and already have recent results for the other markers. A panel lets you assess them together in one blood draw. Compare the included tests and total checkout price, including any ordering or collection fees.
Get your free 30-day heart health guide
Evidence-based steps to optimize your heart health.
