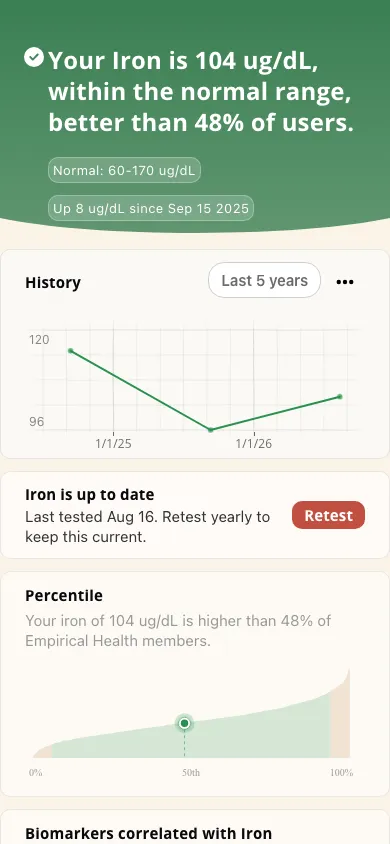
Reference range: 60–170 µg/dL. Lab ranges vary; interpret with ferritin and the other iron studies.
Serum iron measures the iron circulating in your blood, mostly bound to transferrin. It varies throughout the day and after supplements. A normal result does not rule out depleted iron stores; interpret it alongside ferritin, TIBC, and transferrin saturation.
Iron isn't sold on its own. It comes in an iron panel, about $50. A fuller workup adds Ferritin ($45), Vitamin D ($75), hs-CRP ($69), and ApoB ($50). You can test Iron and 100 other biomarkers for $190 as part of an Empirical membership.
Empirical is FSA/HSA eligible, so you can pay with pre-tax dollars. Fast for 8-12 hours beforehand for the most accurate lipid and metabolic results, and expect results in days rather than weeks.
Serum iron measures the iron circulating in your blood, mostly bound to transferrin. It varies throughout the day and after supplements. A normal result does not rule out depleted iron stores; interpret it alongside ferritin, TIBC, and transferrin saturation.
Iron in Empirical, using example data.
No. Serum iron is a snapshot of circulating iron, while ferritin helps assess stored iron. Iron deficiency can develop before hemoglobin falls and anemia appears.
The 2026 ASH guidelines, announced September 16, 2026, use ferritin ≤30 ng/mL to diagnose iron deficiency in most adults, with higher thresholds in some circumstances. In adults with inflammation, ASH suggests measuring both ferritin and TSAT; deficiency may be considered if ferritin <100 ng/mL or TSAT <20%. See our ferritin guide for the population-specific thresholds.
Ferritin is your iron savings account, serum iron is what’s circulating, transferrin carries it, TIBC measures total carrying capacity, and iron saturation tells you what percentage of that capacity is occupied.
Our displayed serum iron reference range is 60–170 µg/dL. Laboratory ranges vary; this range alone does not diagnose or exclude iron deficiency. MedlinePlus: iron tests.
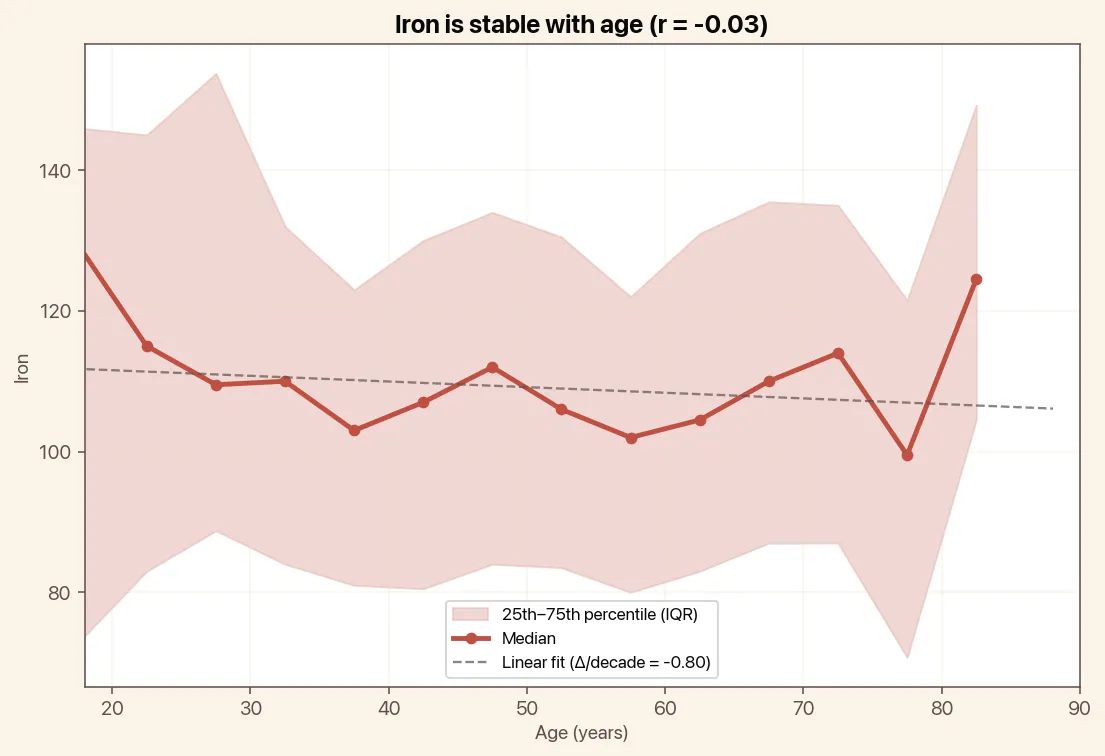
Iron stays relatively flat across adult ages (correlation with age, r = -0.03). Most of the spread in the chart below comes from differences between people rather than from age.

Reference range: 60–170 µg/dL. Lab ranges vary; interpret with ferritin and the other iron studies.
Low serum iron is most commonly caused by iron deficiency from poor dietary intake, blood loss (heavy periods, GI bleeding), or impaired absorption (celiac disease, gastric bypass). Chronic inflammation suppresses iron release from stores, causing low serum iron even when total body iron is adequate.
High serum iron can indicate iron overload from hereditary hemochromatosis, repeated blood transfusions, or excessive supplementation. Iron levels fluctuate throughout the day, so morning fasting samples are most reliable.
Eating iron-rich foods (red meat, poultry, beans, spinach, fortified cereals) helps prevent deficiency. Vitamin C boosts iron absorption, while calcium, tea, and coffee can inhibit it. If you take iron supplements, taking them on an empty stomach with vitamin C improves absorption. Proton pump inhibitors (PPIs) and antacids can reduce iron absorption over time. Women of reproductive age and frequent blood donors should be especially attentive to iron status.
Iron is most highly correlated with Mean Corpuscular Hemoglobin and High-sensitivity C-reactive Protein. Here are the top biomarkers correlated with Iron, based on 500,000 tests done by Empirical Health.
The percentage shows how strongly two biomarkers move together. A higher number means the relationship is stronger. Green = rises and falls together. Orange = one rises as the other falls.
Iron is drawn at 2,200+ Quest and BioReference patient service centers across the US, so there's usually one within a short drive. Browse the full directory to find the one closest to you.
Test your Iron and 100+ other biomarkers in a single blood draw.